Clinical Practice & Governance

When Clinicians Report
Systemic Barriers

Medical professionals describe encountering institutional obstacles when raising alarms about waitlist harms. How early intervention standards were severed from policy execution.

Early-Intervention Window0–6 Yrs
Wait (as of May 2026)Multi-year
Global StandardWHO S.O.C.
SourcesCPS, WHO, Testimonies
Read the clinical record
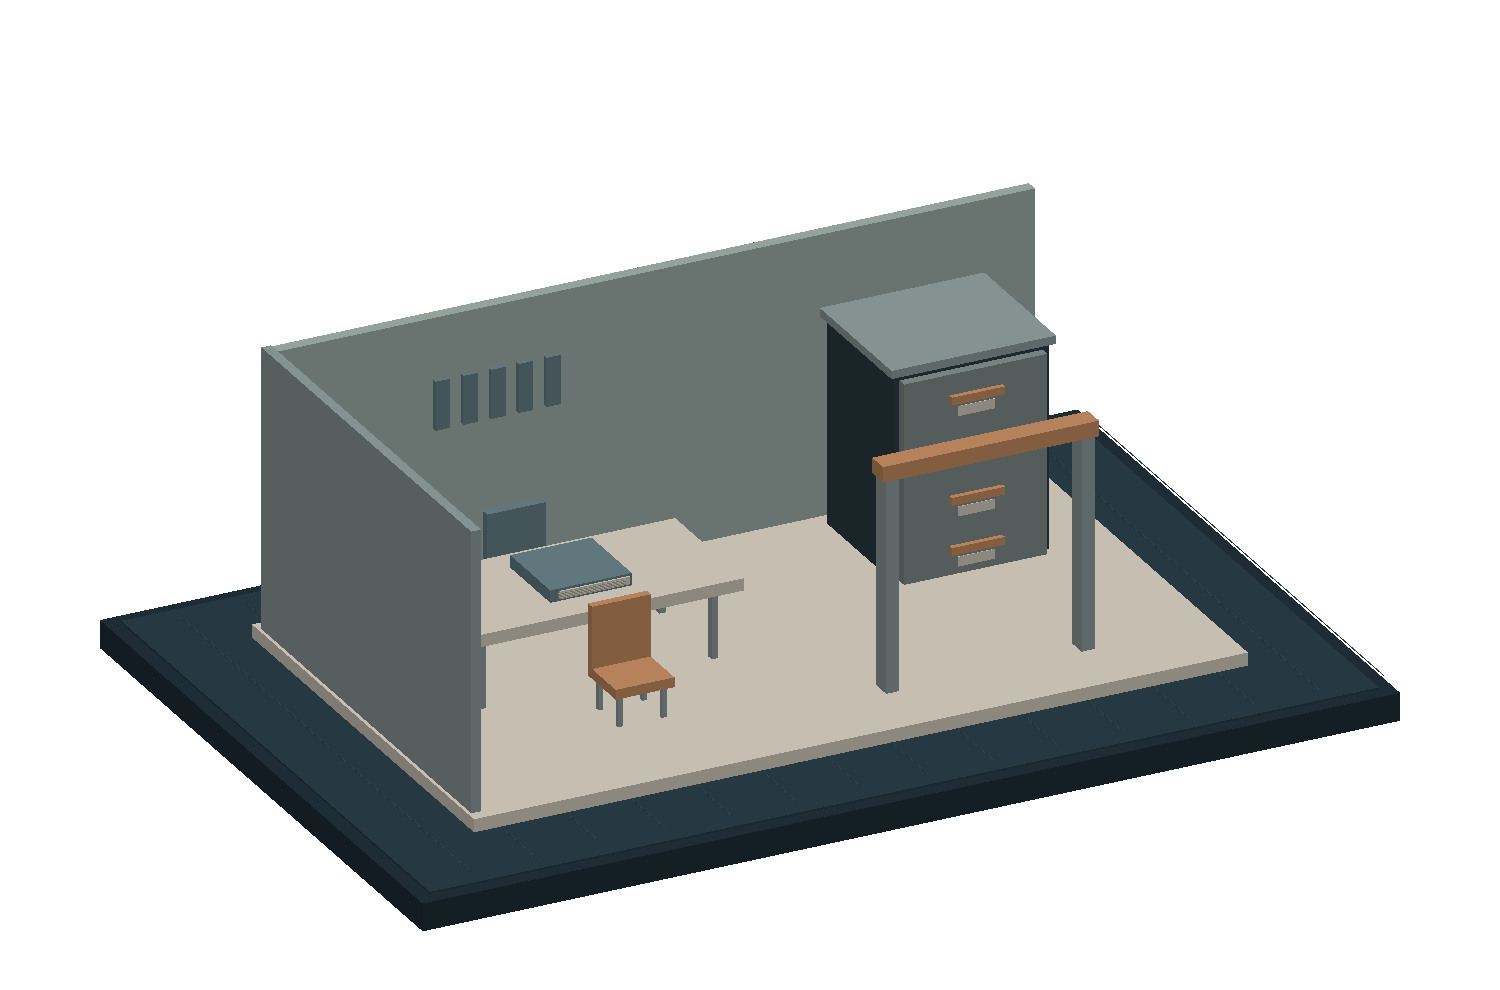
An authored consultation room, records cabinet and open review frame. It depicts relationships, not an identifiable clinic or patient.
Drag to rotate, or use the Rotate and Reset buttons
  • Clinical evidenceDescribe the need and the support being recommended.
  • Program decisionIdentify how that evidence affects the administrative result.
  • Professional voiceExplain the available routes for input and challenge.
Related model
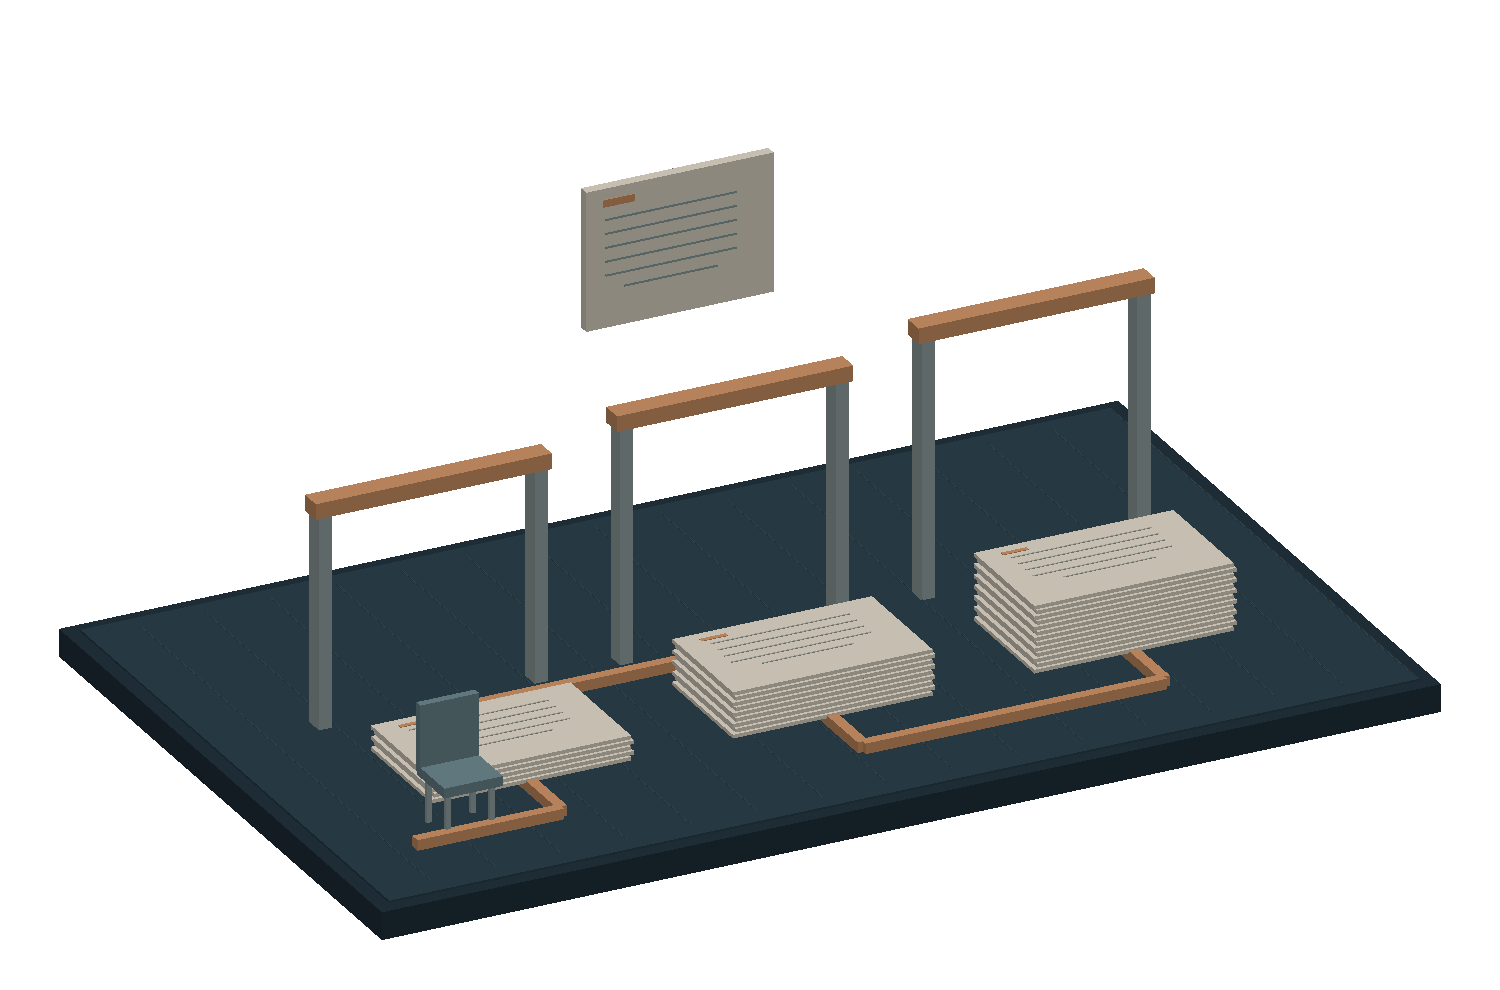
Secondary view: An authored consultation room, records cabinet and open review frame. It depicts relationships, not an identifiable clinic or patient.

Plate 14 · Clinical knowledge & access Conceptual model

An authored consultation room, records cabinet and open review frame. It depicts relationships, not an identifiable clinic or patient. Reported concerns about consultation or professional dependence should remain attributed to their sources. They must not become unsupported claims that every clinician is silenced or that a particular official retaliated. The room is illustrative and is not a clinic or a patient record.

Illustrative model · not evidence
Chapter 01 · The Medical Consensus

The Consensus on Early Intervention

The clinical standard for pediatric autism care is not subject to professional debate. Leading international and domestic pediatric bodies maintain that early intervention delivered immediately following diagnosis produces markedly better lifelong outcomes.

The World Health Organization (WHO) and the Canadian Paediatric Society (CPS) have consistently reaffirmed that early psychosocial and behavioral interventions capitalize on high neural plasticity in young children, establishing fundamental communication, social, and adaptive skills.

Standard of CareWHO

“Timely access to early evidence-based psychosocial interventions can improve the ability of autistic children to communicate effectively and interact socially.”

Clinical WarningCPS

Pediatricians warn that delaying intervention past early childhood leads to secondary complications, skill regression, and heightened family distress that require far more intensive long-term crisis supports.

“I watched children who were speaking at age two lose functional words by age five while waiting for services. When we raise this, we receive form letters.”

Developmental Pediatrician (Anonymized)
Chapter 02 · Institutional Gatekeeping

Four Systemic Barriers Documented by Clinicians

When medical professionals raise concerns regarding waitlist delays and pediatric regression, they describe encountering institutional patterns that insulate policy from clinical scrutiny:

01

Exclusion from Program Design Consultations

During the major 2019 and 2021 redesigns, frontline developmental pediatricians and clinical psychologists reported being excluded from core architecture tables in favor of administrative contractors.

02

Blocked Escalation & Administrative Deflection

Clinicians documenting patient regression on multi-year waitlists report that clinical alert letters to the Ministry received standard form acknowledgments without clinical follow-up.

03

Contractual & Funding Dependencies

Because transfer-payment agencies depend on annual provincial grant renewals, clinical leadership faces structural disincentives against public whistleblowing on wait times.

04

"Not Our Mandate" Jurisdictional Shifting

When pediatricians highlight that delayed therapy causes school crises, responsibility is deflected between MCCSS, the Ministry of Health, and the Ministry of Education.

Chapter 03 · Neurodevelopmental Harm

The Human Cost of Delayed Intervention

When a child waits four to five years for clinical therapy, the entire early childhood neurodevelopmental window is consumed on an administrative waitlist. Clinicians report the recurring downstream consequences:

Clinical ManifestationsAges 5+
  • Language Loss & Skill Regression: Non-verbal and minimally verbal children lose foundational phonetic and communicative attempts.
  • Severe Behavioral Escalation: Frustration from unaddressed communication deficits translates into self-injurious and aggressive behaviors.
  • Caregiver Mental Health Crisis: Extreme caregiving strain without respite leads to parental burnout, career leaves, and family instability.
  • School System Placement Failures: Children enter Kindergarten without prerequisite regulatory tools, resulting in immediate exclusions.
SourcesCPS, WHO, Testimonies
Clinical Evidence Sources

Demand Evidence-Based Autism Care in Ontario

Send this Clinical Brief to your MPP to demand policy aligned with global medical standards.

Sources on this page

The source chain stays visible.

Key claims are paired with their source, evidence tier, and verification date so readers can inspect the public record directly.

Facts4
Sources3

22.5%

Only 20,711 children have active funding agreements (22.5%), less than one in four

Primary sourceMCCSS FOI via OAC · May 2026Verified 2026-08-10
Last system verification: 2026-08-10. Next scheduled update: 2026-11-05.

About this page

See authorship, freshness, trust signals, and ways to stay current.

Written by

Founder & Autism Advocate

Parent of autistic child navigating OAP system
Last updated: