The Burden of Proof.
When care runs on an insurance model, the default answer is no — and the family must prove otherwise. This is how the proving works, who profits from it, and why Ontario, where 71,263 children wait outside the universal system, runs an autism programme built on the same logic.
Insurance model, denials and OAP — data to May 13, 2026.
Read the 30-second brief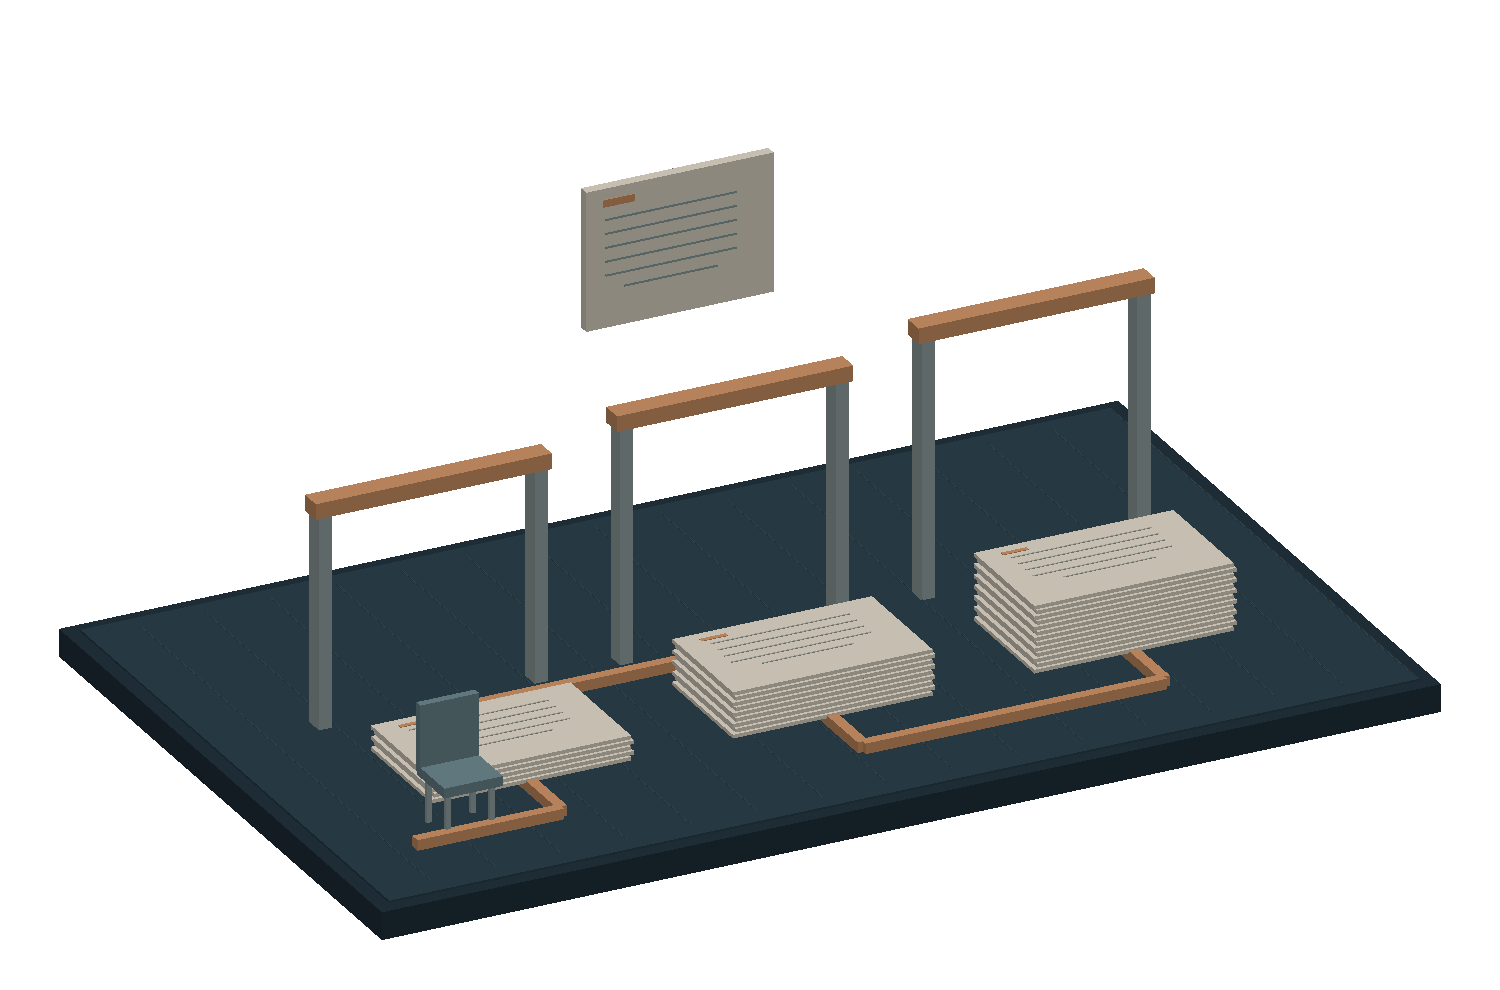
- Initial decisionWhat must a family establish, and under which published rule?
- ReviewWhich part of the decision can the reviewer actually change?
- System evidenceWhat must the program demonstrate about accuracy and fairness?

Plate 04 · Access & insurance Conceptual model
Paper files and successive gates illustrate administrative burden. The number of gates is not a count of OAP requirements. U.S. claims-denial statistics cannot be treated as Ontario Autism Program denial rates. A missed appeal does not, by itself, prove the original decision was correct. The amount of paperwork in the model does not represent a measured number of requirements.
Illustrative model · not evidenceWe are an Ontario organisation, and this report opens with American insurers.
Because Ontario funds autism therapy outside its universal health system, and the programme it built in place of universal coverage behaves like an insurance plan: families register with a privately operated administrator, wait for a funding determination, spend against an individual allocation, and keep receipts for seven years to justify it. 71,263 of 91,974 registered children — 77.5% — are waiting for that funding.
The United States is where the insurance model has run longest, been measured most closely, and left the clearest paper trail: federal transparency data on denial rates, inspector-general audits, peer-reviewed evaluations of what coverage mandates actually cost. It is the best-documented example of what happens to disabled children when the entity deciding a claim is also the entity that keeps the money.
The American evidence in Parts I through V is the control group. Ontario has adopted the administrative architecture without the insurer, and Part VII traces what that has produced here: a $385M annual gap between the $965M budget and the $1.35B the Financial Accountability Office’s methodology implies, absorbed by a queue rather than by a denial letter.
Thirteen findings, each sourced and quotable on its own.
- 01US ACA marketplace insurers denied 19% of in-network claims in 2024 — roughly 85 million of 451 million submitted — with rates ranging from 3% to 36% depending on the insurer, according to KFF’s analysis of federal transparency data.
- 02Fewer than 1% of those denials were appealed: 262,982 internal appeals against roughly 85 million denied claims in 2024, and insurers upheld 66% of the denials that were appealed (KFF).
- 03Only about 5% of in-network claim denials in 2024 cited a lack of medical necessity; roughly a quarter were administrative and more than a third were recorded with no specific reason at all (KFF).
- 04Only 40% of insured US consumers knew they had a legal right to an external appeal, and among marketplace enrollees that fell to 34%, according to a KFF consumer survey.
- 05Of every 100 children referred by a clinician for applied behavior analysis in one Kaiser Permanente Southern California cohort, 13 never received a single hour, 46 were still in therapy at 24 months, and just 28 received the full clinically recommended dose (Choi et al., Journal of Developmental & Behavioral Pediatrics, 2022).
- 06Autism diagnoses are already largely stable at around 14 months of age, yet the median age of earliest known diagnosis in the United States is 47 months, and publicly funded intensive intervention begins an average of nearly three years after diagnosis (Pierce et al. 2019; CDC ADDM 2022 surveillance year; Yingling et al. 2018).
- 07An actuary retained by Oklahoma House leadership projected in 2009 that an autism coverage mandate would raise premiums by 7.8% to 19.8%; the peer-reviewed estimate published that year put the impact at about 1%, and Pennsylvania’s post-mandate spending came to $6,289 per child in 2012 — 17% of the $36,000 cap insurers had warned about.
- 08Every US state and the District of Columbia now mandates autism insurance coverage, but those laws do not reach self-funded employer plans governed by ERISA — and 67% of covered US workers in 2025, including 80% at large firms, were enrolled in exactly those plans (KFF Employer Health Benefits Survey).
- 09Health care administration consumed 34.2% of US health spending in 2017 — $2,497 per person — against 17.0% and $551 per person in single-payer Canada, with insurer overhead alone running $844 per American versus $146 per Canadian (Himmelstein, Campbell & Woolhandler, Annals of Internal Medicine, 2020).
- 10Ontario funds autism therapy outside its universal health system, and as of May 13, 2026 71,263 of 91,974 children registered with the Ontario Autism Program — 77.5% — were still waiting for core clinical funding.
- 11Ontario's autism programme is administered by AccessOAP, a privately operated intake organisation paid roughly $57.9 million a year (Financial Accountability Office of Ontario), and families must retain expense records for seven years so their spending can be reconciled against the funding they received.
- 12Ontario budgets $965M for the Ontario Autism Program in 2026-27 against the $1.35B the Financial Accountability Office's methodology implies is needed — a $385M annual gap that is absorbed by the waiting list rather than by explicit refusals.
- 13Autism therapy sits outside Canada's universal guarantee by law: the Canada Health Act covers medically necessary hospital and physician services, and the Supreme Court of Canada held in Auton v. British Columbia (2004 SCC 78) that ABA/IBI therapy is not among the services it protects — which is why each province designs its own programme.
The Thesis, in Four Lines
- 01. Insurance makes "no" the default. In a universal system, eligibility is the diagnosis. In an insurance system, every claim is contestable, and the burden of proof sits with the claimant.
- 02. The burden is the business model. Fewer than 1% of denied claims are appealed. Every unappealed denial is retained revenue. A system that profits from friction will manufacture friction.
- 03. Ontario imported the architecture without the insurer. The Ontario Autism Program is publicly funded but insurance-shaped: registration through a private administrator, a funding determination, receipts reconciled and kept for seven years — while 77.5% wait.
- 04. Universal systems invert the burden. Canada’s single-payer core runs on a fraction of private insurance overhead. When the payer’s job is to pay rather than to contest, the proving apparatus largely disappears.
The default answer is no. The exception must be proven.
In 2024, US Affordable Care Act marketplace insurers denied 19% of in-network claims — roughly 85 million of 451 million submitted — with individual insurers ranging from 3% to 36%. Only about 5% of denials cited medical necessity. More than a third carried no specific reason at all.
Those figures, drawn from federal transparency data compiled by KFF, describe the machine at rest — its normal operating state, not a scandal year. The same dataset contains the number that explains why the machine persists: of the roughly 85 million denied claims, families appealed 262,982 — under one percent. Of those few appeals, insurers upheld their own denials 66% of the time.
Public-administration researchers Pamela Herd and Donald Moynihan call this administrative burden: the learning costs of decoding what is covered, the compliance costs of assembling documentation, and the psychological costs of being treated as a suspect rather than a claimant. In health care those burdens are not evenly distributed. A national survey published in Health Services Research found 73% of insured US adults performed at least one insurance administrative task in a year — and about one in four delayed or went without care because of one, a barrier the authors found comparable to cost itself. Disabled respondents were nearly three times as likely to carry these tasks.
For autism families the burden compounds, because the service being contested is not an event but a schedule — therapy hours, week after week, each block of hours a fresh opportunity for the payer to ask the parent to prove, again, that their child is still autistic and still improving, or not improving fast enough, or improving too fast to need help. Every re-authorization cycle re-runs the same trial with the same defendant: the family.
The attrition · US marketplace plans, 2024
- In-network claims submitted451 millionEverything the system was asked to pay for in 2024.
- Denied85 million19% of claims submittedOnly about 5% of these denials cited medical necessity.
- Appealed internally262,9820.3% of denialsMore than 99.7% of denials were simply absorbed by the patient.
- Denials actually reversed~89,00034% of appealsInsurers upheld two-thirds of their own denials on internal appeal.
The same four numbers, drawn to true scale
The red band is the 19% denied. The reversals are the sliver beside it — about two hundredths of one percent of all claims, too small to render at this width. The drawing is accurate. That invisibility is the finding. A system in which the correction is 1/950th the size of the error has no real appeals process. Its default answer holds.
View the underlying figures as a table
| Stage | Claims | Share of previous stage |
|---|---|---|
| In-network claims submitted | 451 million | — |
| Denied | 85 million | 19% of claims submitted |
| Appealed internally | 262,982 | 0.3% of denials |
| Denials actually reversed | ~89,000 | 34% of appeals |
Source: KFF, Claims Denials and Appeals in ACA Marketplace Plans in 2024 (March 2026), from federal transparency data. Claims submitted, denied, and appealed are KFF figures. The reversal count is an ETWO calculation applying KFF’s finding that insurers upheld 66% of denials on internal appeal to the 262,982 appeals filed; it is an estimate, not a published total.
The obvious question about that funnel is why almost nobody appeals. The answer is not that patients accept the decision. In a KFF survey of insured consumers, only 40% believed they had a legal right to have a denial reviewed by a government agency or an independent expert; 51% were unsure. Among marketplace enrollees — the population in the denial figures above — awareness fell to 34%.
A right that two-thirds of the people holding it do not know they have is a formality. The appeals process satisfies the requirement that a remedy exist while the denial rate behaves as though one does not.
- Claims Denials and Appeals in ACA Marketplace Plans in 2024. KFF · March 2026
- Kyle & Frakt, “Patient administrative burden in the US health care system.” Health Services Research · 2021
- Herd & Moynihan, “Health care administrative burdens: Centering patient experiences.” Health Services Research · 2021
Denial is industrialized. Appeal is artisanal.
In 2023, ProPublica and The Capitol Forum published internal Cigna documents describing a review system called PXDX, under which company doctors could deny batches of claims without opening the patient files. Over two months in 2022, the system was used to deny 300,000 claims — an average of 1.2 seconds of review per claim. Cigna told reporters the process was legal and applied to low-cost claims. That defence is worth sitting with: the proving apparatus pointed at families operates in seconds when pointed by the payer.
For autism specifically, ProPublica’s 2024 reporting on UnitedHealth Group’s Optum unit described internal strategy documents for limiting spending on applied behavior analysis — the most commonly prescribed autism therapy — in the Medicaid plans it manages. The documents describe applying a “more rigorous” clinical review to ABA in roughly 20 states, culling providers from the network, and authorizing fewer therapy hours than clinicians requested — while the company projected spending about $290 million on ABA in its Medicaid plans that year, and its parent reported $22 billion in annual net profit. A related Optum program for limiting outpatient therapy was ruled unlawful by courts or regulators in three states, per the same reporting.
None of this machinery is confined to one company. The American Medical Association’s 2024 survey found practices completing 39 prior-authorization requests per physician per week, with 93% of physicians reporting that prior authorization delays necessary care. When federal inspectors audited Medicare Advantage prior-authorization denials for post-acute care, they found 95% of appealed nursing-facility denials were overturned. And the federal agencies that police mental-health parity reported to Congress in 2026 that the most common violation remains exactly the one autism families know best: stricter prior authorization and utilization review for behavioral care than for medical care.
- ProPublica / The Capitol Forum, “Congressional Committee, Regulators Question Cigna System That Lets Its Doctors Deny Claims Without Reading Patient Files” · May 2023
- ProPublica, “UnitedHealth Is Strategically Limiting Access to Critical Treatment for Kids With Autism” · December 2024
- AMA 2024 Prior Authorization Physician Survey (n=1,000)
- HHS Office of Inspector General reports on Medicare Advantage prior-authorization denials · June 2026
Before the money runs out, the clock does.
The cohort · Choi et al., 2022
- Referred for ABA by a clinician100
A doctor has already decided this child needs the therapy.
- Received any ABA at all87
13 of every 100 referred children never got a single hour.
- Still in therapy at 12 months66
A third are gone inside the first year.
- Still in therapy at 24 months46
Fewer than half remain at two years.
- Received the full recommended dose28
The dose the evidence base for ABA is actually built on.
View the underlying figures as a table
| Stage | Per 100 referred |
|---|---|
| Referred for ABA by a clinician | 100 |
| Received any ABA at all | 87 |
| Still in therapy at 12 months | 66 |
| Still in therapy at 24 months | 46 |
| Received the full recommended dose | 28 |
Source: Choi KR, Bhakta B, Knight EA, et al., “Patient Outcomes After Applied Behavior Analysis for Autism Spectrum Disorder,” Journal of Developmental & Behavioral Pediatrics 43(1):9–16 (2022). All five stages come from this one cohort. A separate study of a different Kaiser region (Croen et al., 2017) found 23% of referred children never initiated ABA; that figure describes another population and is not combined with these.
The denial statistics in Part II describe paperwork. This is what the paperwork does to a childhood. In a cohort of 4,145 children referred for ABA inside a single large US health system, researchers followed what happened next: 13% never received any ABA at all, 66% were still in therapy at twelve months, 46% at twenty-four, and 28% received the full clinically recommended dose — the dose the evidence base for the therapy is actually built on. A separate study of a different Kaiser region found 23% of referred children never initiated treatment, and that only 15% received at least 80% of their recommended hours.
The second clock starts earlier and runs longer. Autism can be identified far sooner than it usually is: Pierce and colleagues found that a diagnosis made at around 14 months is already largely stable, with stability rising through the second year. The median American child is diagnosed at 47 months. Then, in the publicly funded systems studied by Yingling and colleagues, an average of nearly three more years passes between diagnosis and the start of intensive intervention.
Put those together and the child who could have started at eighteen months frequently starts near seven. That interval is not neutral waiting; it is the interval the clinical evidence identifies as the one that matters most. The Early Start Denver Model trial recorded a 17.6-point IQ gain against 7.0 in the comparison group for toddlers starting between 18 and 30 months, and a later cost analysis of the same model found it cost about $14,000 more per year while it ran and saved roughly $19,000 per child per year afterwards. The system is not only failing the child. It is declining a return it has already been shown.
- Choi et al., “Patient Outcomes After Applied Behavior Analysis for ASD.” J Dev Behav Pediatr · 2022
- Pierce et al., “Evaluation of the Diagnostic Stability of the Early Autism Spectrum Disorder Phenotype.” JAMA Pediatrics · 2019
- Shaw et al., “Prevalence and Early Identification of ASD Among Children Aged 4 and 8 Years, ADDM Network 2022.” MMWR Surveillance Summaries · 2025
- Yingling, Hock & Bell, “Time-Lag Between Diagnosis of ASD and Onset of Publicly-Funded EIBI.” J Autism Dev Disord · 2018
The burden of proof has a price. Families pay it twice.
Mothers of children with autism earn 56% less than mothers of children with no health limitation — about $14,755 a year — and their families earn 28% less overall, a penalty the researchers attribute to the unpaid work of arranging and supervising care that no one else will coordinate.
The direct costs stack on top. In national US data, families of children with autism were more likely than other special-needs families to spend ten or more hours a week providing or coordinating care and to have paid more than $1,000 out of pocket in a year. Even in states that forced insurers to cover autism therapy, families in the highest-spending fifth still paid over $200 a month out of pocket for ASD-specific services.
The legislative record is its own indictment. Insurers did not cover autism therapy until every state and DC passed a law compelling them to, a campaign that ran from Indiana in 2001 to Tennessee in 2019 — and when those mandates arrived, use of autism services among commercially insured children measurably rose, which is another way of saying children had been going without. Where mandates carried age caps, service use fell the month the cap hit, by coverage rule rather than by clinical need. And state parity laws — the promise that behavioral care would be treated like medical care — showed no demonstrable improvement in access for autism families in the peer-reviewed evaluation; families in strict-parity states were 61% more likely to report four-figure out-of-pocket spending.
Even a mandate, an in-network provider, and a willing clinician do not close the loop. In a large California health system operating under a state mandate, 13% of children referred for ABA never received a single hour of it, and only 28% received a full clinical dose. The apparatus of proving, authorizing, re-authorizing and reconciling consumes families before it ever pays them.
The burden of proof is defended, annually, at scale.
Autism coverage in the United States was not granted; it was extracted. Beginning with Indiana in 2001 and ending with Tennessee in 2019, every state and the District of Columbia eventually passed a law forcing insurers to cover autism services — a state-by-state campaign fought over eighteen years against the documented opposition of the industry’s trade association. AHIP’s public argument — that mandates raise premiums and thereby “reduce access to affordable coverage” — reframed paying for disabled children’s therapy as a threat to everyone else’s insurance.
The industry’s weapon in those fights was the cost projection, and the record now lets us score them. In Oklahoma in 2009, an actuary retained for House leadership warned legislators that the proposed mandate, “Nick’s Law,” would raise premiums by 7.8% to 19.8%; the state’s own employee insurance board put it at 1% or less, and the bill died in committee. The peer-reviewed estimate published that same year by Bouder, Spielman and Mandell landed at about 1%, with an upper bound of 2.31%. The insurer-side figure was high by roughly an order of magnitude, and it worked anyway: Oklahoma parents later filed a professional-conduct complaint over the analysis.
What the mandates actually cost is now measurable. Across state-employee plans the reported cost of adding autism coverage was $0.15 per member per month in the first year and $0.31 in the second — figures collected by Autism Speaks, an advocacy organization, and reported in the Harvard Law & Policy Review, so worth treating as directional rather than independent actuarial work. The independent confirmation is Pennsylvania’s: after its mandate, actual autism-related spending came to $6,289 per child in 2012 — 17% of the $36,000 annual cap insurers had warned about. Meanwhile the peer-reviewed evaluations found exactly what compulsion was supposed to achieve: treated prevalence rose, service use and spending per child increased, and the board-certified behaviour-analyst workforce grew from 1.34 to 29.88 per 100,000 children between 2003 and 2017.
There is a catch that makes the entire mandate story narrower than it sounds. State insurance mandates do not reach self-funded employer plans, which are governed by the federal ERISA statute instead. In 2025, 67% of covered US workers — and 80% of those at large firms — were in exactly such plans. The hardest-won consumer protection in autism coverage does not legally apply to two-thirds of the people who assume it protects them.
The lobbying that defends this architecture is a line item. In 2024 the insurance industry spent approximately $155 million on federal lobbying — one industry, one year, one country. The Affordable Care Act’s medical-loss-ratio rules cap what insurers may retain at 15–20% of premium for administration and profit; on the industry’s scale that retained share is measured in hundreds of billions. A company the size of UnitedHealth Group — $447.6 billion in 2025 revenues — does not need to deny any individual claim in bad faith for the arithmetic to work. It needs only a system in which proving is slow, appealing is rare, and the default is no.
Universal systems do not have this problem. They have a different one.
The counter-model is universal health care, and the comparison is largely settled in the literature. Himmelstein, Campbell and Woolhandler measured administrative overhead across the US and Canada in Annals of Internal Medicine: in 2017, health care administration consumed 34.2% of US health spending ($2,497 per person) versus 17.0% in single-payer Canada ($551 per person). The largest gap was precisely where the proving happens: insurer overhead ran $844 per American against $146 per Canadian.
A universal system operates on a fundamentally different legal and economic logic. The coverage pool is the population. The premium is the tax base. Because the payer has no commercial imperative to minimize payouts and no competitors to defend against, the machinery of proving — prior authorization, concurrent review, eligibility renewal — is radically reduced. In a universal system, the diagnosis is the eligibility. The proving apparatus largely disappears because its economic function does.
This does not make universal systems flawless; they are characterized by wait times for elective and specialist care, a tradeoff Canada accepts in exchange for eliminating financial ruin at the point of service. But they are uniquely efficient at precisely the thing the insurance model is bad at: moving resources to patients with chronic, complex, or developmental needs without forcing them to assemble a defensive dossier.
- Access requires constant demonstration of need.
- Every step (referral, auth, care) carries friction.
- Financial risk is shifted to the patient.
- Payer profits directly from unused allocations.
- Administrative overhead (US) ~34% of spending.
- Diagnosis equals eligibility.
- Friction is minimized by design.
- Financial risk is absorbed by the tax base.
- Payer has no profit motive to deny care.
- Administrative overhead (Canada) ~17% of spending.
- Himmelstein, Campbell & Woolhandler, “Health Care Administrative Costs in the US and Canada.” Annals of Internal Medicine · 2020
- Auton (Guardian ad litem of) v. British Columbia (Attorney General), 2004 SCC 78
A waiting list is a denial executed via time.
The OAP currently reports 91,974 registered children. Of those, 71,263 — 77.5% — are waiting for core clinical funding.
The Financial Accountability Office of Ontario (FAO) calculated that to actually serve the waitlist under the current model would require an annual budget of roughly $1.35B. The province’s 2026-27 allocation is $965M. That $385M gap is the mathematical reason the waitlist exists. The programme does not have the funds to authorize the care it promises.
Rather than sending 71,263 denial letters, the system absorbs the shortfall through duration. This is the danger of administrative burden removed from its American context: it obscures the structural failure. An insurer’s denial is an explicit, actionable refusal. A five-year waitlist is a passive refusal that masquerades as an administrative process. For the developing child, the distinction is entirely theoretical.
Answers & Clarifications
Is it legal for US insurers to deny claims automatically?
Under US law (including the Affordable Care Act and ERISA), insurers are generally required to provide a “full and fair review” of claims. However, investigative reporting and regulatory actions have repeatedly exposed systems (like Cigna's PXDX) that use algorithms to identify claims for denial, which are then signed off by medical directors in seconds. Regulators argue this violates the spirit, and often the letter, of the requirement for individualized review.
How does Ontario's administrative cost compare to the US?
Because the Ontario Autism Program operates outside OHIP (the universal health insurance plan), its specific administrative overhead is difficult to isolate from broader ministry budgets. However, we know AccessOAP, the private consortium administering the intake, is paid roughly $57.9 million annually. This represents the cost of operating an insurance-like intake and reconciliation apparatus for a single condition.
What happens when a child in Ontario ages out of the OAP?
The OAP serves children up to age 18. If a child spends years on the waitlist, those years are simply lost. The funding allocations are age-banded (meaning younger children generally receive higher maximums), so a child who waits until age 10 not only loses the early intervention window but also ages into a lower funding bracket.
Stop waiting. Start acting.
Ontario families assembled this evidence from the government’s own records. Put it to work — email your MPP in two minutes.